

Choosing the wrong research topic costs more time than any other decision in your final project, and most students make it in the first week without knowing what they are choosing against.
MGT675 and HCM600 are both final projects, and they want opposite things from a topic. One needs a question you can collect data about. The other needs a question other people have already published enough about to review systematically.
This guide gives you 108 topics built for those constraints — 58 for MGT675 and 50 for HCM600 — and every one has been tested before it went on the page. For the review topics we searched for existing systematic reviews; for the MGT675 topics we checked both the literature base and whether you could realistically collect the data in a semester.
Thirteen more topics failed badly enough that we removed them, and you will find them named at the end of each list with the reason. The 108 that remain each carry a status and, where the ground is already well covered, the angle that is still open.
Get Help Choosing Your Research Topic
The Two Projects Want Opposite Things
This is the single most useful thing on this page, so it comes first.

| MGT675 Research Project | HCM600 Research Project | |
| Type of research | Applied primary research | Systematic review, PRISMA method |
| Your data | You collect it — surveys, interviews, organisational records | Published studies. You collect no new data |
| A topic fails if | You cannot get access to the people or the data | Too few published studies exist to review |
| A topic also fails if | It is so broad no single study could answer it | It is so broad the search returns thousands of papers |
| Structure | Introduction · Literature Review · Methodology · Analysis and Results · Discussion and Conclusion | Background and Objectives · Review Methods · Review Results · Discussion, then Conclusion, Limitations and Recommendations |
| Key appendices | Instruments, data tables | PRISMA checklist and full search strategy |
The practical consequence. A topic like “the effect of a new safety checklist at my hospital” is a good MGT675-style project and an impossible HCM600 one, because nobody has published on your hospital. A topic like “the effectiveness of surgical safety checklists on post-operative mortality” is a good HCM600 review and a poor MGT675 project, because you cannot collect that data yourself in a semester.
Test Your Topic Before You Commit
For MGT675 — the access test
- Can you actually reach the people? If your design needs 200 responses from hospital managers, do you have a route to 200 hospital managers?
- Will the organisation let you? Data from your employer usually needs permission in writing. Ask before you build a project on it.
- Can one study answer it? “How does leadership affect performance” cannot. “How does transformational leadership relate to retention among nurses at three Riyadh hospitals” can.
- Is there enough literature for Chapter 2? Primary research still needs a literature review. A topic nobody has written about leaves Chapter 2 empty.
- Can you finish it in the time you have? Ethics approval, data collection and analysis all take longer than students plan for.

For HCM600 — the evidence test
- Search it before you choose it. Run your terms in PubMed. If you get fewer than roughly 15 relevant studies, the review will be thin. If you get 3,000, the topic is too broad.
- Is there a defined intervention and a defined outcome? Systematic reviews compare something against something. “Quality in hospitals” has neither.
- Has someone already reviewed it? Check Cochrane and PROSPERO. A recent identical review is a reason to narrow or shift, not to proceed.
- Are the studies in English and accessible? You need full text, not just abstracts.
- Can you write inclusion and exclusion criteria for it? If you cannot say precisely what counts, you cannot screen consistently, and screening is most of the work.
Spend a day on this. Running your search terms before you commit to a topic is the highest-return hour in the whole project. Students who skip it discover the problem in Chapter 2 and start again.
How We Tested These Topics
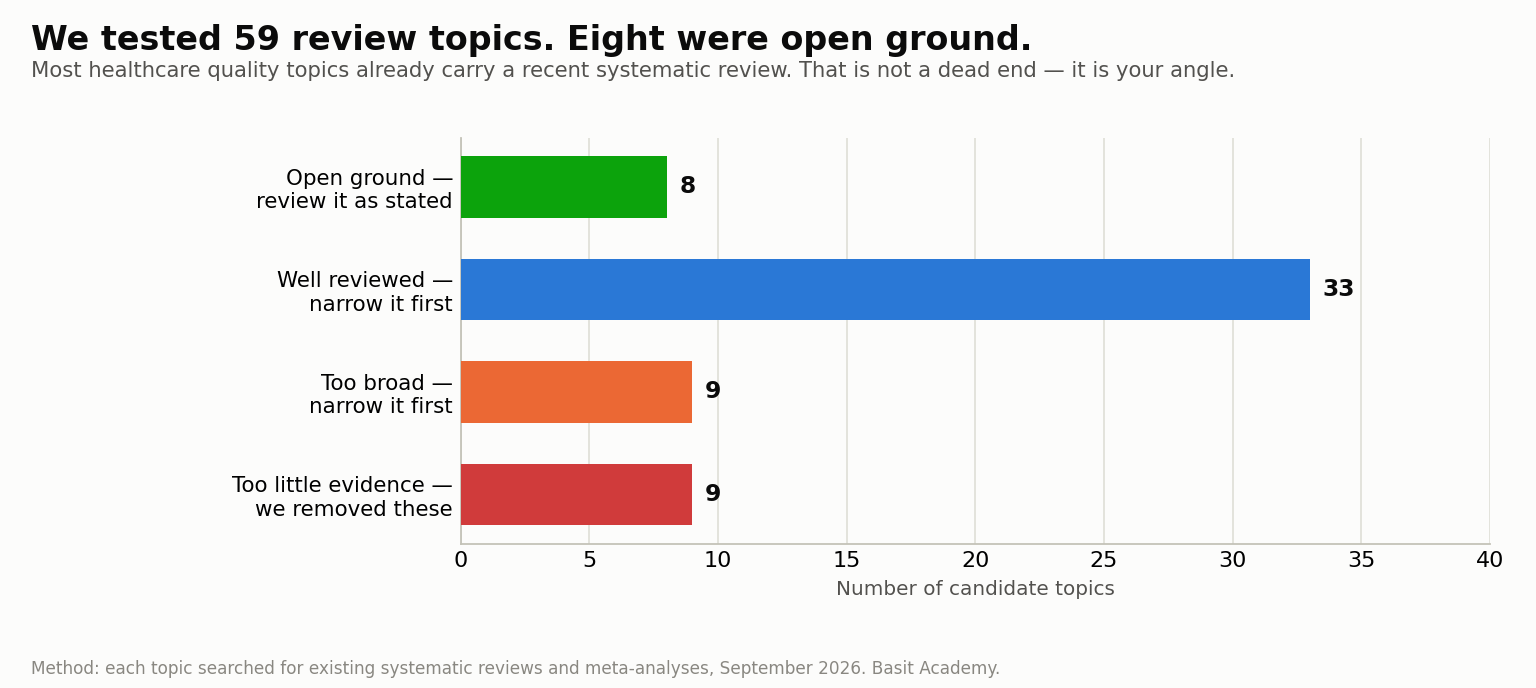
Every topic below was checked before it went on this page. That is not standard for a topic list and it changes what the list is worth.
For the HCM600 review topics we searched each one for existing systematic reviews and meta-analyses. Of 59 candidates, only eight were open ground. Thirty-three already carry a recent review, nine were too broad to screen, and nine had too little extractable evidence to review at all — those nine are not on this page.
For the MGT675 topics we tested 62 and kept 58. We checked two things: whether a literature base exists, ideally including Saudi or Gulf studies, and whether a working student could realistically collect the data in one semester. Several strong-sounding topics failed on access rather than literature, and those have been rewritten with a reachable population rather than dropped.
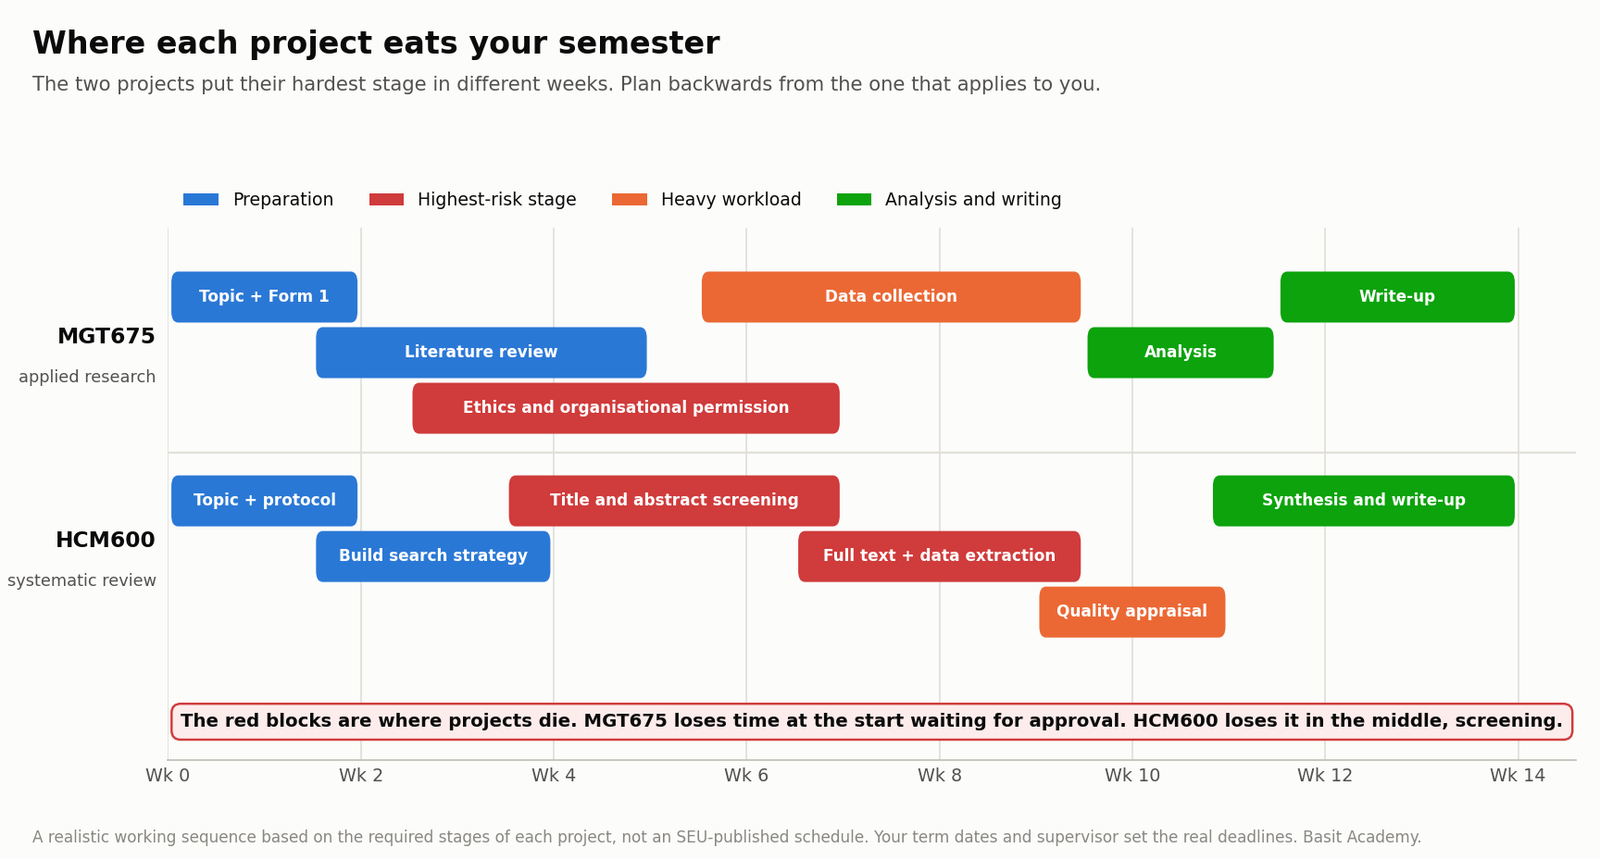
The access test and the evidence test also land in different weeks, which is the second thing to plan around. An MGT675 project loses time at the front, waiting on ethics and organisational permission. An HCM600 review loses it in the middle, screening. Whichever project you are on, the stage that will hurt is predictable, and you can start it earlier than you think.
“Already reviewed” is not a dead end — it is your angle. A topic with three existing reviews has a deep primary literature and a clear gap: a setting, a population, an outcome or a date range nobody has covered. The narrowing column below is where the actual research value of this page sits.
58 Research Topics for MGT675
Applied primary research in a Saudi or Gulf setting. Status tells you whether the topic works as written or needs the change in the last column.
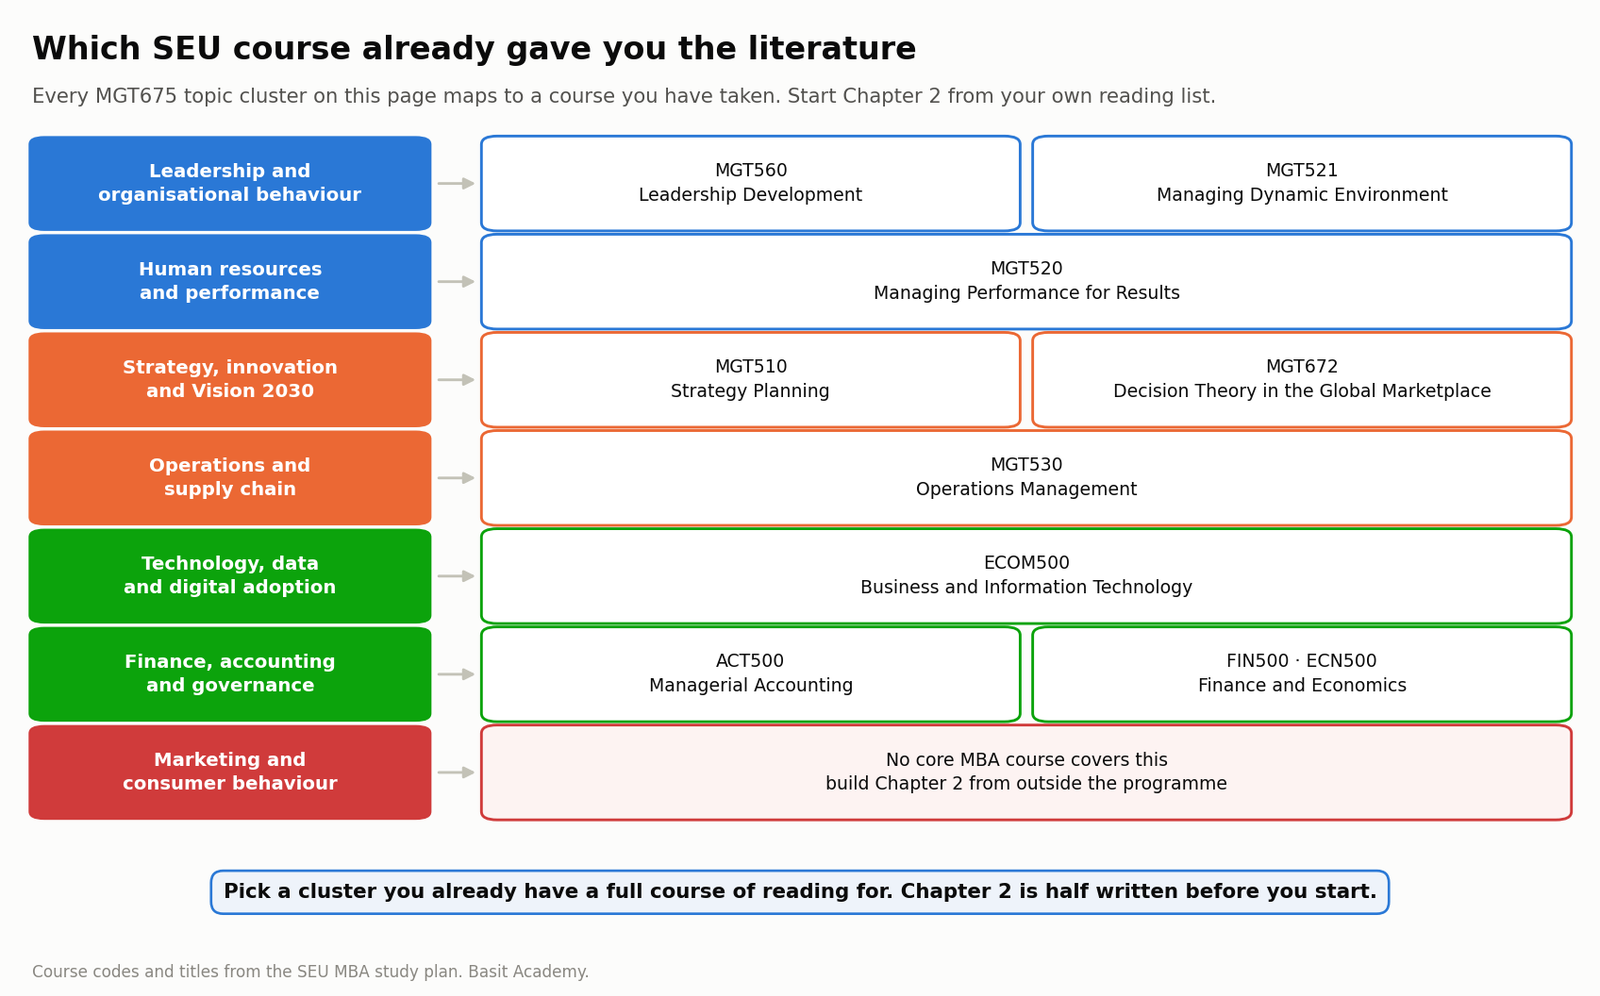
Before you scan the list, one shortcut. Every cluster below maps onto a course you have already passed, which means the reading for Chapter 2 is sitting in a folder you already own.
Leadership and organisational behaviour
| Topic | Status | What to do |
| Transformational leadership and nurse retention in Saudi private hospitals | Open | Deep Saudi nursing-leadership literature. Budget 4–8 weeks for hospital ethics sign-off unless you work there |
| Remote working and team cohesion in Saudi financial services | Open | Works best from inside a bank or fintech. Otherwise recruit across firms via professional networks |
| Leadership style and engagement in family-owned Saudi businesses | Open | No register of family-firm status exists — define it by respondent-reported family ownership and recruit 3–5 firms |
| Psychological safety and error reporting in Saudi healthcare | Reframed | Originally set in manufacturing, where the Gulf literature is thin. In healthcare the evidence base is strong |
| Career barriers for women in middle management in Saudi corporates | Open | Rich Saudi glass-ceiling literature. 12–18 interviews via professional networks is a realistic semester |
| Gen Z versus Millennial motivation drivers in one Saudi sector | Narrowed | “Generational differences” across all cohorts needs quota samples you cannot reach. Two adjacent cohorts, one sector, works |
| Job rotation and employee satisfaction in Saudi banking | Open | Screen for staff who actually experienced rotation, or the analysis collapses |
Human resources and performance
| Topic | Status | What to do |
| Annual versus continuous appraisal and motivation in one Saudi sector | Narrowed | “Appraisal frequency and motivation” had no population attached. Name the sector |
| Saudization policy and recruitment practice — HR officers and recent Saudi hires | Reframed | HR directors set policy and are gated one firm at a time. Recruiters and recent hires are reachable across firms |
| Perceived training effectiveness and self-rated performance in Saudi SMEs | Reframed | Owners will not disclose training spend or productivity figures. Perception measures are collectable |
| Turnover drivers in the Saudi hospitality sector | Open | Strong Saudi hotel literature. Needs one or two HR gatekeepers and a bilingual questionnaire |
| Flexible working and retention intention among Saudi working mothers | Open | Population self-selects readily. Use retention intention, not actual turnover |
| Compensation structure and supervisor-rated sales performance in Saudi retail | Reframed | Objective sales data sits in company systems. Supervisor ratings inside one chain are obtainable |
Strategy, innovation and Vision 2030
| Topic | Status | What to do |
| Digital transformation readiness in Saudi mid-sized enterprises | Open | Good recent Saudi literature. One respondent per firm, reachable via Monshaat networks |
| Strategy awareness and implementation barriers among Saudi public sector employees | Reframed | Surveying a named ministry needs its own approval. Public-sector employees generally are reachable |
| Barriers to entrepreneurship among Saudi graduates | Open | Very deep Saudi entrepreneurial-intention literature, and the most reachable population available |
| Local content requirements and supplier strategy — contractor procurement managers | Qualitative only | Peer-reviewed Saudi local-content work is scarce. Run it as 10–12 interviews and lean on the wider localisation literature |
| Innovation capability and firm performance among Saudi SMEs | Broadened | Firm-level tech-sector designs need 80–120 separate firms. Broadening to SMEs makes the sample achievable |
| Public-private partnership success factors — contractor and consultant project managers | Reframed | Project directors and NCP officials are gated. Their counterparts on the delivery side are not |
Operations and supply chain
| Topic | Status | What to do |
| Supply chain disruption response among Saudi healthcare supply professionals | Reframed | Pharma distribution alone is a narrow community. Widening to healthcare providers opens the sample |
| Lean implementation and operational efficiency in Saudi manufacturing | Open | Established Saudi lean literature. One plant manager as gatekeeper makes it very doable |
| Supplier perceptions of Etimad evaluation criteria in Saudi public procurement | Flipped | Procurement officials need per-entity permission. Suppliers are reachable and have the same information |
| Customer satisfaction with certified versus non-certified providers in one service category | Narrowed | ISO 9001 generally is too broad. One category — private clinics, training centres, logistics agents — works |
| Delivery service quality and customer satisfaction in Saudi last-mile logistics | Reframed | Operational performance data is company-held. The customer or courier side is collectable |
Marketing and consumer behaviour
| Topic | Status | What to do |
| Social media marketing effectiveness for Saudi SMEs | Open | The best-supported topic in this set. Excellent current Saudi literature, reachable respondents |
| Consumer trust in Saudi e-commerce | Crowded | Very deep literature and consumers are easy to reach — but heavily researched. Add an angle: social commerce, or AI-generated reviews |
| Influencer marketing and purchase intention among Saudi youth | Crowded | Extensive recent Saudi evidence. Bring a fresh moderator or mediator or you risk a replication |
| Brand loyalty in the Saudi telecommunications market | Open | Established literature and no gatekeeper at all — subscribers are universal |
| Buy-now-pay-later adoption and spending behaviour in Saudi Arabia | Open | Literature is recent rather than deep but sufficient. Anchor in UTAUT2 or TPB |
| Customer experience and retention in Saudi food delivery apps | Open | Saudi studies using PLS-SEM already exist. Clean topic, universal population |
Finance, accounting and governance
These four use Tadawul-listed company data, which is public. That makes them archival rather than primary research, so each needs a primary component added — usually six to ten interviews with finance managers explaining the patterns you found. Check with your supervisor whether a purely archival design is accepted.
| Topic | Status | What to do | |
| Working capital management and profitability in Saudi listed companies | Add primary | Abundant literature, accessible data. Add 6–8 finance manager interviews | |
| Corporate governance disclosure and firm value on Tadawul | Add primary + cap scope | Hand-coding a disclosure index is 40–60 hours. Cap at 30–50 firms over three years | |
| ESG reporting among Saudi listed firms | Add primary + data warning | Refinitiv and Bloomberg ESG scores are paywalled. Build the index from published sustainability reports or the project stalls | |
| Capital structure in Saudi family firms | Add primary | Classifying family-firm status from ownership disclosures is judgement-heavy and must be defended in your methodology | |
| Topic | Status | What to do | |
| Financial literacy and investment behaviour among Saudi professionals | Open | Multiple Saudi studies. Reachable through your own network, clean survey design | |
| Fintech adoption among Saudi small business owners | Open | Strong current Saudi literature, well-established adoption models | |
| Current VAT perceptions and category-level spending adjustment | Reframed | VAT was introduced in 2018 — asking about the introduction now is recall bias. Current perceptions are researchable | |
| Islamic finance products and SME funding access in Saudi Arabia | Open | Screen for owners who have actually sought financing, or you are surveying opinions rather than access | |
| Cost management practice and perceived performance in Saudi firms | Split the design | Decide at proposal stage whether this is archival Tadawul work or a survey of finance staff. Trying to be both halfway through is how this one fails | |
Technology, data and information systems
This cluster did not exist on the old page and it is where the most reachable populations are. Every topic here surveys users rather than executives, which removes the gatekeeper that kills most MBA projects.
| Topic | Status | What to do |
| Cybersecurity policy compliance among Saudi employees | Open | Measure compliance intention, not incidents. Incident data is confidential and no employer will release it to a student |
| Employee acceptance of AI in HR decisions in Saudi organisations | Reframed | Survey employees, not HR directors. Directors are gated one firm at a time; employees are reachable across many |
| E-government service quality and citizen satisfaction in Saudi Arabia | Open | The easiest population on this page. Absher and Tawakkalna users are everywhere and no gatekeeper stands between you and them |
| ERP implementation success in one named Saudi organisation | Access risk | Scope it to user-perceived success inside one organisation you already have a route into. Multi-firm ERP studies need CIO access you will not get |
| Data-driven decision culture and perceived performance in one Saudi sector | Narrowed | Name the sector and build a real sampling frame before you commit. “Saudi firms” is not a population you can draw a sample from |
Cross-cultural management and organisational change
| Topic | Status | What to do |
| Expatriate adjustment and job performance in Saudi Arabia | Open | Use self-rated or peer-rated performance. Supervisor ratings need the employer to take part, and that is a different project |
| Cross-cultural team effectiveness in Saudi multinational subsidiaries | Reframed | Run it at individual level with snowball recruitment. Team-level designs need whole intact teams, which no employer hands over |
| Cultural intelligence and leadership effectiveness in Saudi organisations | Reframed | Have subordinates rate the leader. Self-rated leadership effectiveness is the weakest design available and markers know it |
| Readiness for change in one Saudi sector during one named reform | Narrowed | “Vision 2030 change readiness” is not a researchable question. Name the sector and the specific change. Arabic-validated readiness scales already exist |
| Employee resistance to change in Saudi financial services and fintech | Broadened | Banking alone is a small, heavily gatekept population. Widening to financial services and fintech makes the sample achievable |
Engagement, wellbeing and the employment relationship
| Topic | Status | What to do |
| Knowledge sharing and innovative work behaviour in Saudi organisations | Open | Well-supported constructs, validated Arabic scales, respondents reachable across firms. One of the safest designs here |
| Employer branding and employment intention among Saudi graduates | Open | The best access on the whole page — your own university is the sampling frame, and no permission chain stands in the way |
| Green HRM practices and employee environmental behaviour in Saudi firms | Open | A growing Saudi literature, an individual-level survey and no organisational gatekeeper |
| Work-life balance and turnover intention among Saudi healthcare staff | Access risk | Hospital ethics approval runs 4–8 weeks. Private clinics, or non-clinical hospital staff, shorten that considerably |
| Occupational stress and job satisfaction among Saudi teachers | Access risk | Ministry of Education approval for public schools is slow. Private schools or university faculty are reachable without it |
Sustainability, CSR and entrepreneurship
| Topic | Status | What to do |
| Corporate social responsibility and consumer loyalty in Saudi Arabia | Open | A consumer-side design with a universal population and a solid Saudi literature behind it |
| Sustainability practices among Saudi SMEs | Qualitative only | Run it as 12–15 interviews with owner-managers. A survey needs a public sampling frame of SMEs, and there is not one |
| Perceived ecosystem support and entrepreneurial persistence among Saudi founders | Reframed | Startup survival cannot be measured in a semester and failed founders are unreachable by definition. Perceived support and persistence intention can both be measured now |
| Service quality and revisit intention at Saudi heritage and entertainment destinations | Open | A post-visit online survey. You do not need a tourism authority to take part, and they will not reply in time anyway |
Four topics we removed. “NEOM investment and regional labour markets” has no accessible population and almost no peer-reviewed base — it is a macroeconomics question, not a student project. “Warehouse automation and order accuracy” depends on private warehouse management records no student will be given. “Budgeting practice in Saudi SMEs” and “activity-based costing in Saudi service firms” both fail twice over: the Saudi literature is thin, and they require access to the finance function, which is the most closely guarded department in any company.
50 Research Topics for HCM600
PRISMA systematic reviews. Status tells you whether the topic is open ground or already reviewed — and where an existing review exists, the last column gives you the angle that is still available.
Patient safety interventions
| Topic | Status | Your angle |
| Barcode medication administration and medication error rates | Open ground | Few existing reviews against many primary before-and-after studies. Could focus on non-ICU wards or workaround-related errors |
| Surgical safety checklists and post-operative complications | Well reviewed | Restrict to MENA or Gulf hospitals, or make checklist compliance level the exposure rather than checklist use |
| Rapid response teams and in-hospital cardiac arrest outcomes | Well reviewed | Paediatric rapid response teams, or afferent-limb failure, or post-2018 studies in non-Western health systems |
| Hand hygiene interventions and infection rates | Too broad | Three Cochrane iterations exist. Pick one setting (ICU or ED) plus one infection outcome, or the post-COVID period only |
| Structured handover tools and communication failures | Well reviewed | One transition point — ICU to ward, or theatre to recovery — with omission-rate outcomes and controlled designs only |
| Inpatient fall prevention programmes | Well reviewed | Acute hospital wards only, since the Cochrane review pools care facilities too. Or patients with cognitive impairment |
| Pressure ulcer prevention bundles and incidence | Well reviewed | ICU or surgical patients only, or bundles with a defined repositioning or nutrition component |
Quality improvement methods
| Topic | Status | Your angle |
| Six Sigma and laboratory turnaround time | Open ground | The main review covers Lean, leaving Six Sigma and DMAIC under-reviewed. Expect uncontrolled before-and-after studies, so plan a narrative synthesis |
| Lean methodology and emergency department waiting times | Open ground | Viable as stated. Post-2015 studies with quantitative door-to-doctor or length-of-stay outcomes |
| Clinical audit and physician guideline adherence | Well reviewed | Cochrane covers 140+ trials. Pick one clinical target such as antibiotic prescribing, or Gulf hospitals specifically |
| Care bundles and sepsis mortality | Well reviewed | One-hour versus three-hour bundle, or emergency-presenting sepsis, or paediatric populations |
| Clinical pathways and hospital length of stay | Well reviewed | One condition — hip fracture, COPD, CABG — or an explicit update of the 2010 Cochrane review |
Health information technology
| Topic | Status | Your angle |
| Clinical decision support and prescribing errors | Well reviewed | Paediatric weight-based dosing, antimicrobial prescribing, or ambulatory care. Do not also pick the CPOE topic — the source studies overlap almost completely |
| Alert fatigue and clinician response to safety warnings | Well reviewed | Shift from measuring prevalence to evaluating interventions that reduce overrides — tiering, role-tailoring — using controlled studies only |
| Mobile health apps and medication adherence | Well reviewed | One condition such as hypertension or type 2 diabetes, with objective adherence measures. Or Arabic-language apps and MENA users |
| Electronic health records and medication safety | Too broad | Pick one component (CPOE, decision support, e-MAR) or one outcome (adverse drug event rate), or study the go-live period specifically |
| Telemedicine and chronic disease management | Too broad | Umbrella reviews already exist. One condition plus one outcome — HbA1c in type 2 diabetes — or Gulf populations |
Workforce, culture and human factors
| Topic | Status | Your angle |
| Safety culture interventions and incident reporting rates | Open ground | Existing reviews report culture scores; the reporting-rate outcome is comparatively unreviewed. Few studies use controlled designs — say so in your limitations |
| Shift length and clinical error rates | Open ground | The main review dates from 2015. Frame yours explicitly as a 2015-to-2026 update, nurses only |
| Nurse staffing ratios and patient mortality | Well reviewed | ICU only, or failure-to-rescue rather than crude mortality, or mandated-ratio policy changes as natural experiments |
| Nurse burnout and patient safety incidents | Well reviewed | One incident type such as medication errors, or Gulf settings, or longitudinal designs only |
| Simulation-based training and clinical team performance | Well reviewed | One specialty — obstetric emergencies, trauma — or in-situ simulation only, or patient outcomes rather than performance scores |
| Interprofessional team training and patient outcomes | Well reviewed | Restrict to studies reporting actual patient outcomes. Most report training reactions only, and that subset is genuinely small |
| Interventions to reduce workplace violence against healthcare staff | Well reviewed | Organisational interventions only — staffing levels, security, environmental design. Exclude staff training, which dominates the existing reviews, and use incident rates rather than attitudes |
Accreditation, governance and policy
| Topic | Status | Your angle |
| Hospital accreditation and quality of care outcomes | Well reviewed | The strongest fit on this page for an SEU student. Restrict to Saudi or Gulf hospitals — CBAHI and JCI — or to one outcome such as mortality or infection rates |
| Public reporting of performance data and hospital quality improvement | Well reviewed | Post-2020 studies only, or non-US health systems, or one mechanism such as market share versus internal response |
| Pay-for-performance and clinical quality indicators | Well reviewed | A post-2019 update of the Cochrane review, or non-OECD schemes, or patient-safety indicators specifically |
Patient experience and outcomes
| Topic | Status | Your angle |
| Care transition programmes and 30-day readmissions | Well reviewed | Heart failure or COPD only, or one named model. Do not also pick discharge planning — same trial pool, same outcome |
| Medication reconciliation at discharge and post-discharge errors | Well reviewed | Older patients with polypharmacy, or technology-assisted reconciliation, or post-2019 studies |
| Shared decision-making tools and patient outcomes | Well reviewed | One decision context such as cancer screening — and swap satisfaction for decisional conflict or regret, which are measured far more consistently |
| Health literacy interventions and chronic disease self-management | Well reviewed | One condition such as type 2 diabetes, or teach-back as the sole intervention, or Arabic-speaking populations |
| Patient-reported outcome measures in quality improvement programmes | Well reviewed | Service-level PROM feedback rather than individual-level, and one specialty such as oncology or orthopaedics |
| Patient engagement and treatment adherence | Too broad | Both terms are umbrella constructs. Define engagement as one concrete intervention — patient portal, teach-back, self-management coaching — plus one condition |
Infection prevention and care bundles
Bundles are the most heavily reviewed area in patient safety, so almost every topic here arrives already reviewed. That is workable — the pooled reviews draw on Western ICUs, and Gulf settings are genuinely under-represented in them.
| Topic | Status | Your angle |
| Central line bundles and CLABSI rates | Well reviewed | Restrict to adult ICUs in GCC or Middle Eastern hospitals. The global reviews pool settings that do not resemble yours |
| Ventilator-associated pneumonia bundles and ventilator-associated events | Well reviewed | Gulf or Middle East settings, or isolate one bundle component — oral chlorhexidine, or subglottic secretion drainage |
| Surgical site infection bundles and infection rates | Well reviewed | Pick one procedure. Caesarean section is the cleanest: a defined population, a consistent outcome and a large trial base |
| Neonatal care bundles and preventable harm | Too broad | Name one harm — NICU CLABSI, unplanned extubation, or admission hypothermia. “Preventable harm” cannot be screened for |
| Antimicrobial stewardship programmes and prescribing | Too broad | Restrict to outpatient or primary care in GCC countries. Inpatient stewardship already carries several recent reviews |
Deterioration, escalation and emergency care
| Topic | Status | Your angle |
| Interventions to reduce diagnostic error in emergency departments | Open ground | Fix one intervention class — decision support, structured reflection, or mandatory second review. Without that you are reviewing a field, not a question |
| Maternal early warning systems and severe maternal morbidity | Open ground | Frame it as effectiveness, and exclude model-development papers at screening or you will drown in validation studies |
| Early warning scores and escalation of care | Well reviewed | Make the escalation process the exposure, not the score’s accuracy. Most reviews test prediction; very few test what happens after the trigger |
| Emergency department crowding interventions and patient outcomes | Well reviewed | Pick one mechanism — fast-track streams, full-capacity protocols, or boarding limits. Middle Eastern EDs narrow it further |
| Triage systems and emergency department outcomes | Well reviewed | Compare CTAS and ESI in Middle Eastern EDs. Avoid the triage-training angle — a protocol registered in 2025 already occupies it |
Maternal, neonatal and primary care quality
| Topic | Status | Your angle |
| Accreditation of primary healthcare centres in the GCC | Open ground | The standout topic on this page. CBAHI accredits primary healthcare centres and almost nothing has been published reviewing the effect. This is genuinely unoccupied ground for an SEU student |
| Quality improvement collaboratives and maternal-newborn outcomes | Well reviewed | Restrict to low- and middle-income or Middle Eastern settings, where the pooled effect is least established |
| Antenatal care quality improvement and birth outcomes | Too broad | Name one intervention — group antenatal care, or a birth-preparedness package — and one outcome |
Prediction, artificial intelligence and medication safety
A warning specific to this cluster. The artificial intelligence literature in healthcare is overwhelmingly model development and validation, not evaluation. If you do not exclude those papers explicitly in your criteria, your search will return thousands of results and almost none of them will have an outcome you can extract.
| Topic | Status | Your angle |
| Pharmacist-led medication review and adverse drug events | Well reviewed | Restrict to the emergency department or the point of admission, with 90-day readmission related to an adverse drug event as the outcome |
| Machine learning sepsis prediction and patient outcomes | Well reviewed | Include only deployed systems reporting patient outcomes. Exclude model-development and validation studies, which are the bulk of the literature |
| Artificial intelligence decision support and clinician performance | Too broad | One specialty, randomised trials only. Anything wider is unscreenable |
| Patient portals and health outcomes | Too broad | One condition plus one objective outcome — HbA1c, or blood pressure control. Portal use alone is not an outcome |
Nine topics we removed, and why it matters that we did. PDSA cycles, just culture and reporting, clinical governance structures, never-event policies, open disclosure and patient trust, radiology report turnaround time, critical test result notification, antibiotic time-outs, and deprescribing as a general subject. In each case the published work is qualitative, conceptual, definitional, or already covered by a 2025 umbrella review — there is plenty written about these subjects and almost nothing new with extractable outcome data. A student who picks one will screen for weeks and then discover they cannot build a results table. That is the most expensive mistake available in this project.
Where to Search — and What Will Get Your Review Rejected
This is where the two projects diverge most sharply, and getting it wrong is expensive.
| Project | Use these | Do not build on these |
| HCM600 systematic review | PubMed / MEDLINE, CINAHL, Scopus, Web of Science, Cochrane Library, and the Saudi Digital Library | News sites, business magazines, market research summaries, blogs. A PRISMA review excludes them at screening |
| MGT675 applied research | Scopus, Web of Science, Business Source, JSTOR, Emerald, ScienceDirect, plus Tadawul filings and official statistics for data | Unattributed market statistics and secondary summaries of studies you have not read |
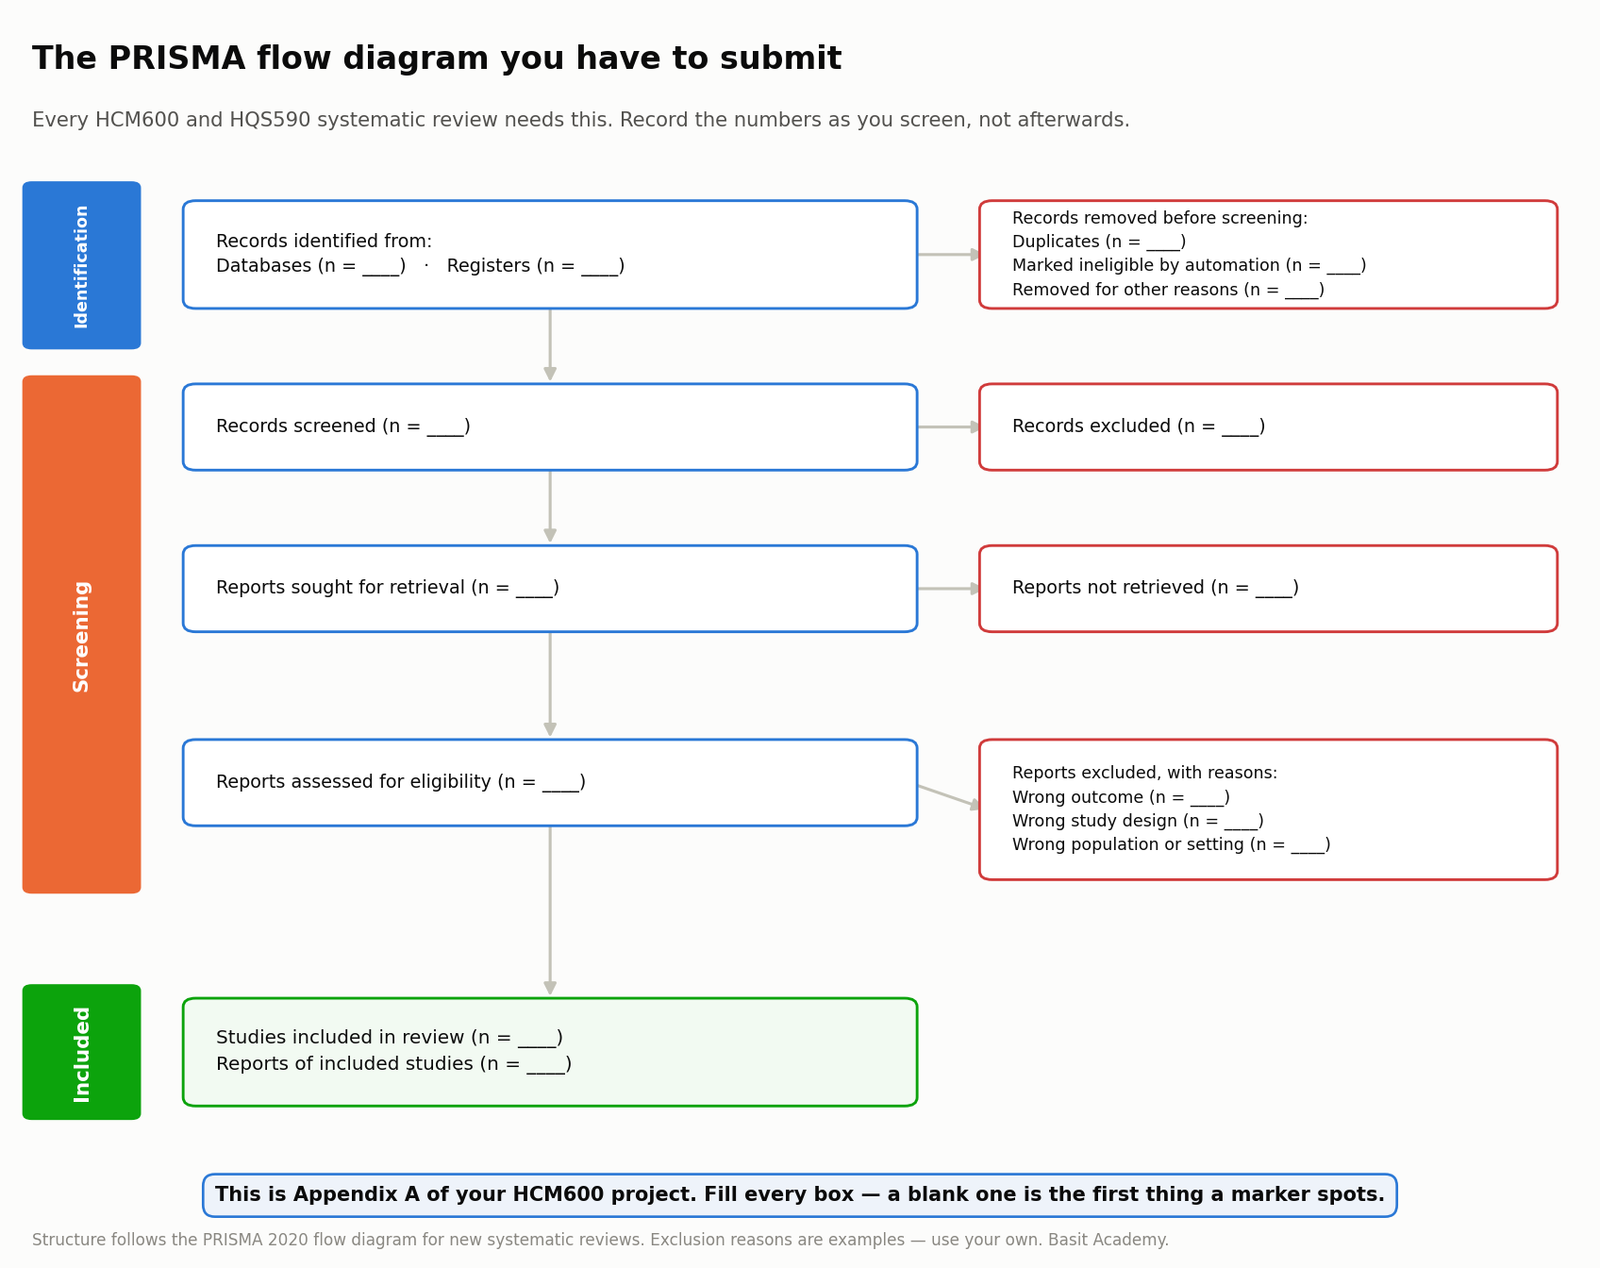
For HCM600 specifically, your search strategy is not background work — it is Appendix B of your submitted project, presented as a six-column table recording each database, your keywords with Boolean operators, the date range, and how many results you found and included. Build it as you go. Reconstructing it afterwards is painful and it shows.
The flow diagram above is the other half of the same requirement. It is Appendix A, and every number in it has to reconcile with your search table. The only reliable way to produce it is to record each count at the moment you make the decision — how many duplicates you removed, how many titles you excluded, how many full texts you could not retrieve. Students who leave it to the end end up guessing, and a flow diagram whose numbers do not add up is the easiest thing in the project for a marker to catch.
Grey literature has a place, carefully. WHO, the Saudi Ministry of Health, CBAHI and the Institute for Healthcare Improvement publish reports that can legitimately inform a healthcare review. Say in your methods whether you included grey literature and why. What you cannot do is cite a news article as evidence of effectiveness.
Topics to Avoid, and Why
- Anything you cannot narrow to one intervention and one outcome. “Improving healthcare quality” is a field, not a research question.
- Your own workplace, for HCM600. It is the right instinct and the wrong project. Save it for a quality improvement initiative; a systematic review needs published studies.
- Topics with a recent identical review. Check PROSPERO and Cochrane first. Finding one after you have screened 400 abstracts is the worst version of this mistake.
- Anything requiring patient data you cannot access. Ethics approval for patient records is not a semester-length process.
- COVID-19 as a standalone subject. The literature is enormous, uneven in quality and fast-dating. It works as context, rarely as the whole topic.
- Topics where the evidence is all from one health system. A review of interventions studied only in the US may not transfer, and you will have to say so in your limitations anyway.
Where Exploratory Essays Actually Fit
Exploratory writing has a real place in your degree, and it is earlier than this page previously suggested.
An exploratory essay examines a question from several angles without committing to one conclusion. That is genuinely useful when you are still deciding what to research — it is a way of finding out whether a topic has enough in it before you commit a semester to it.
What it is not is preparation for the projects themselves. MGT675 asks you to defend a finding. HCM600 asks you to follow a protocol and synthesise what the evidence says. Both require the conclusion an exploratory essay deliberately withholds.
| Stage | What to write | Why |
| Deciding on a topic | Exploratory writing | Tests whether the question has enough in it, from several angles |
| Writing the proposal | A focused argument | Form 1 and Form 2 need a defined question, not an exploration |
| The project itself | Structured research | Both projects require a defended conclusion |
So use exploratory writing to choose. Do not use it to submit.
Frequently Asked Questions
What makes a good MGT675 research topic?
One you can collect data about. A management question narrow enough for a single study, in an organisation or sector you can actually reach, with enough published literature to support Chapter 2.
What makes a good HCM600 research topic?
One with a defined intervention and a defined outcome, and enough published studies to review. Search your terms in PubMed before you commit — roughly 15 to a few hundred relevant results is the workable range.
Can I use the same topic for both?
Almost never. They need opposite things. A topic you can collect original data on is usually under-published, and a topic with a rich published evidence base is usually too large to study yourself.
Can I research my own hospital or employer for HCM600?
No. HCM600 is a systematic review of published studies. Your own organisation is the right subject for a quality improvement project, not for a review.
How many studies does a systematic review need?
There is no fixed number, and your screening process determines it rather than the reverse. If your search returns fewer than about fifteen relevant studies, the topic is probably too narrow.
Which databases should I use for HCM600?
PubMed or MEDLINE, CINAHL, Scopus, Web of Science and the Cochrane Library, plus the Saudi Digital Library. News and business sites do not meet systematic review inclusion criteria.
Do I need ethics approval for MGT675?
If you are collecting data from people, usually yes, and organisational permission on top. Start that process early — it is the most common cause of a delayed project.
How do I know if someone has already reviewed my HCM600 topic?
Search PROSPERO, the systematic review registry, and the Cochrane Library. A recent identical review means narrow your question or change it.
Can Basit Academy help me choose a topic?
Yes. Topic selection is where we can save you the most time, because a topic that fails the access test or the evidence test costs weeks to discover on your own.
Get Help With Your Research Project
The topic decision is the one that shapes everything after it. If you are weighing two or three ideas, that is exactly the point at which a conversation saves the most time.
Basit Academy works with SEU students on both projects — MGT675 applied research and HCM600 systematic reviews. Qualified tutors, human written, never AI.